
RESEARCH PAPER
Prevalence of periodontitis in HIV-positive patients on highly active antiretroviral therapy: an observational study
1
Manipal College of Dental Sciences Mangalore, Manipal Academy of Higher Education, Manipal, Karnataka, India
2
Department of Periodontology, Manipal College of Dental Sciences Mangalore, Manipal Academy of Higher Education, Manipal, India
Submission date: 2024-03-13
Final revision date: 2024-05-30
Acceptance date: 2024-05-30
Publication date: 2026-09-25
Corresponding author
Neetha J. Shetty
Manipal College of Dental Sciences, Mangalore, Manipal Academy of Higher Education, MCODS, LHH Road, Hampankatta, 575001, Mangalore, India
Manipal College of Dental Sciences, Mangalore, Manipal Academy of Higher Education, MCODS, LHH Road, Hampankatta, 575001, Mangalore, India
KEYWORDS
TOPICS
ABSTRACT
Introduction:
The study aimed to evaluate the severity and prevalence of periodontitis in HIV-positive patients on highly active antiretroviral therapy (HAART).
Material and methods:
Twenty seven individuals aged between 25 and 55 years, with more than fifteen permanent teeth excluding third molars were included in the study, and periodontal status of patients was assessed.
Results:
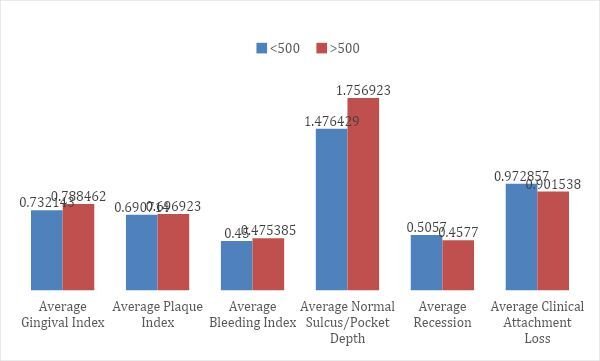
The average GI was 0.76 ± 0.53, and the average PI was 0.69 ± 0.36. The average bleeding index recorded according to Mombelli sulcular bleeding index was 0.46 ± 0.43, the average normal sulcus/pocket depth was 1.61 ± 0.53, and the average recession was 0.48 ± 0.42. The most common therapy administered was tenofovir, lamivudine, and dolutegravir (TLD) 30 in 10 patients (37%), followed by 5 patients on TLD 90 (18.5%), 5 patients on tenofovir, lamivudine + atazanavir/ritonavir (TL + ATV/r) (30 + 30), and 4 patients on TLD 60 (14.8%).
Conclusions:
Periodontitis was observed in 26 patients (96.3%) with the absence of periodontitis in 1 of the 27 patients examined (3.7%). The current investigation demonstrates that HIV-positive individuals under HAART present a high prevalence of mild to moderate periodontitis. According to the study's conclusions, tooth loss was consistently affected by the administration of cART. Therefore, treating physicians should routinely recommend patients to oral health professionals to maintain dental health and provide higher quality of life for HIV-infected patients.
REFERENCES (25)
1.
Mataftsi M, Skoura L, Sakellari D. HIV infection and periodontal diseases: an overview of the post-HAART era. Oral Dis 2011; 17: 13-25.
2.
Ravi JR, Rao TR. Estimation of prevalence of periodontal disease and oral lesions and their relation to CD4 counts in HIV seropositive patients on antiretroviral therapy regimen reporting at District General Hospital, Raichur. J Indian Soc Periodontol 2015; 19: 435-439.
3.
Fokam J, Geh BKN, Sosso SM, Takou D, Ngufack ES, Nka AD, et al. Determinants of periodontitis according to the immunological and virological profiles of HIV-infected patients in Yaoundé, Cameroon. BMC Oral Health 2020; 20: 359. DOI: 10.1186/s12903-020-01353-7.
4.
Ryder MI, Nittayananta W, Coogan M, Greenspan D, Greenspan JS. Periodontal disease in HIV/AIDS. Periodontol 2000 2012; 60: 78-97.
5.
Gonçalves LS, de Carvalho Ferreira D, Vidal F, Souza RC, Gonçalves C, Pavan P, et al. Stage II and stage III periodontitis clinical burdens of HIV-1 undergoing antiretroviral therapy. Clin Oral Investig 2022; 26: 2187-2195. Erratum: Clin Oral Investig 2022; 26: 4239.
6.
Groenewegen H, Bierman WFW, Delli K, Dijkstra PU, Nesse W, Vissink A, et al. Severe periodontitis is more common in HIV-infected patients. J Infect 2019; 78: 171-177.
7.
Lauritano D, Moreo G, Oberti L, Lucchese A, Di Stasio D, Conese M, et al. Oral manifestations in HIV-positive children: a systematic review. Pathogens 2020; 9: 88. DOI: 10.3390/pathogens9020088.
8.
Eggleton JS, Nagalli S. Highly Active Antiretroviral Therapy (HAART). In: StatPearls. Treasure Island (FL): StatPearls Publishing; 2022.
9.
Coogan MM, Greenspan J, Challacombe SJ. Oral lesions in infection with human immunodeficiency virus. Bull World Health Organ 2005; 83: 700-706.
10.
Brady LJ, Walker C, Oxford GE, Stewart C, Magnusson I, McArthur W. Oral diseases, mycology and periodontal microbiology of HIV-1-infected women. Oral Microbiol Immunol 1996; 11: 371-380.
11.
Alpagot T, Duzgunes N, Wolff LF, Lee A. Risk factors for periodontitis in HIV patients. J Periodontal Res 2004; 39: 149-157.
12.
Ranganathan K, Umadevi M, Saraswathi TR, Kumarasamy N, Solomon S, Johnson N. Oral lesions and conditions associated with human immunodeficiency virus infection in 1000 South Indian patients. Ann Acad Med Singap 2004; 33 (4 Suppl): 37-42.
13.
Akmatov MK, Hu E, Rüsenberg R, Kollan C, Schmidt D, Kohring C, et al. Areas with high HIV prevalence: A spatial analysis of nationwide claims data in Germany. HIV Med 2024; 25: 498-503.
14.
Bravo IM, Correnti M, Escalona L, Perrone M, Brito A, Tovar V, et al. Prevalence of oral lesions in HIV patients related to CD4 cell count and viral load in a Venezuelan population. Med Oral Patol Oral Cir Bucal 2006; 11: E33-E39.
15.
Eke PI, Dye BA, Wei L, Thornton-Evans GO, Genco RJ; CDC Periodontal Disease Surveillance workgroup. Prevalence of periodontitis in adults in the United States: 2009 and 2010. J Dent Res 2012; 91: 914-920.
16.
Bodhade AS, Ganvir SM, Hazarey VK. Oral manifestations of HIV infection and their correlation with CD4 count. J Oral Sci 2011; 53: 203-211.
17.
Schätzle M, Löe H, Lang NP, Bürgin W, Anerud A, Boysen H. The clinical course of chronic periodontitis. J Clin Periodontol 2004; 31: 1122-1127.
18.
Tukutuku K, Muyembe-Tamfum L, Kayembe K, Odio W, Kandi K, Ntumba M. Oral manifestations of AIDS in a heterosexual population in a Zaire hospital. J Oral Pathol Med 1990; 19: 232-234.
19.
Masouredis CM, Katz MH, Greenspan D, Herrera C, Hollander H, Greenspan JS, et al. Prevalence of HIV-associated periodontitis and gingivitis in HIV-infected patients attending an AIDS clinic. J Acquir Immune Defic Syndr (1988) 1992; 5: 479-483.
20.
Caton JG, Armitage G, Berglundh T, Chapple ILC, Jepsen S, Kornman KS, et al. A new classification scheme for periodontal and peri-implant diseases and conditions – introduction and key changes from the 1999 classification. J Clin Periodontol 2018; 45 Suppl 20: S1-S8. DOI: 10.1111/jcpe.12935.
21.
Pólvora TLS, Nobre ÁVV, Tirapelli C, Taba M Jr, de Macedo LD, Santana RC et al. Relationship between human immunodeficiency virus (HIV-1) infection and chronic periodontitis. Expert Rev Clin Immunol 2018; 14: 315-327.
22.
Highfield J. Diagnosis and classification of periodontal disease. Aust Dent J 2009; 54 Suppl 1: S11-S26. DOI: 10.1111/j.1834-7819.2009.01140.x.
23.
Fricke U, Geurtsen W, Staufenbiel I, Rahman A. Periodontal status of HIV-infected patients undergoing antiretroviral therapy compared to HIV-therapy naive patients: a case control study. Eur J Med Res 2012; 17: 2. DOI: 10.1186/2047-783X-17-2.
24.
Umeizudike KA, Ayanbadejo PO, Savage KO, Nwhator SO, Akanmu AS, Ogunleye O. Comparative periodontal status of human immunodeficiency virus-positive patients and controls in a dedicated human immunodeficiency virus clinic in Nigeria. Niger J Clin Pract 2016; 19: 35-40.
25.
Vernon LT, Demko CA, Whalen CC, Lederman MM, Toossi Z, Wu M, et al. Characterizing traditionally defined periodontal disease in HIV+ adults. Community Dent Oral Epidemiol 2009; 37: 427-437. Erratum: Community Dent Oral Epidemiol 2010; 38: 96, 190.
Share
RELATED ARTICLE
| eISSN: | 1732-2707 |
| ISSN: | 1730-1270 |

We process personal data collected when visiting the website. The function of obtaining information about users and their behavior is carried out by voluntarily entered information in forms and saving cookies in end devices. Data, including cookies, are used to provide services, improve the user experience and to analyze the traffic in accordance with the Privacy policy. Data are also collected and processed by Google Analytics tool (more).
You can change cookies settings in your browser. Restricted use of cookies in the browser configuration may affect some functionalities of the website.
You can change cookies settings in your browser. Restricted use of cookies in the browser configuration may affect some functionalities of the website.
